Cardiology
1961
Factors of Risk in the Development of Coronary Heart Disease (Framingham Heart Study)
Six-year follow-up of the Framingham cohort linked high blood pressure, high cholesterol and electrocardiogram abnormalities to coronary disease and brought the term "risk factor" into medical use, giving preventive cardiology its working vocabulary.
Key people
- William Kannel
- Framingham investigator from its early years, lead author of the 1961 report and later the study's third director
- Thomas Dawber
- Second director of the Framingham study, from 1950
- William Castelli
- Fourth director of the Framingham study, from the late 1970s
- Ancel Keys
- Physiologist whose diet-heart hypothesis the Framingham data helped support
Source
By the 1940s cardiovascular disease was the leading cause of death in the United States, yet cardiology had almost no way to predict who would develop it. The U.S. Public Health Service designed it to find the factors predisposing to coronary disease in an ordinary population. The Framingham Heart Study began in 1948 and recruited 5,209 residents of Framingham, Massachusetts, aged 28 to 62, between 1948 and 1952. More than half were women, unusual for the epidemiological studies of the time.
William Kannel, who led the analytic work on the first major outcome report, and Thomas Dawber, who had directed the study since April 1950, published their six-year findings in Annals of Internal Medicine in 1961. The paper showed that high blood pressure, elevated serum cholesterol and electrocardiogram abnormalities each predicted coronary disease. Cigarette smoking had been linked to heart disease in a Framingham report the year before. The 1961 paper brought the phrase 'risk factor' into medical use to describe these measurable antecedents, giving clinicians a new vocabulary.
The reception was not uniformly enthusiastic. Many physicians doubted the epidemiological approach itself: in 1961 there was resistance to creating a Council on Epidemiology at the American Heart Association, and critics questioned whether Framingham residents represented Americans in general. The role of dietary fat and cholesterol was also disputed; Ancel Keys, who had described high cholesterol in coronary patients, was its best-known advocate.
The risk-factor idea soon became arithmetic. In 1967 Truett, Cornfield and Kannel combined seven factors in one model and found a 30-fold (men) to 70-fold (women) difference in coronary incidence between the highest and lowest tenths of risk. The study itself nearly closed: in 1969 the NIH ordered it phased out, private donors and President Nixon kept it alive, and from 1971 it ran under a federal contract with Boston University.
The cohort itself expanded over time, enrolling the children of the original participants in 1971 and a grandchildren cohort in 2002. In 1977 Framingham investigators reported that higher HDL cholesterol went with less coronary disease, and William Castelli, the fourth director, reported with colleagues in 1983 that weight gain raised cardiovascular risk. From 1976 Framingham risk profiles let physicians calculate an individual patient's predicted risk of a cardiovascular event.
Keep exploring
 Read next · led to
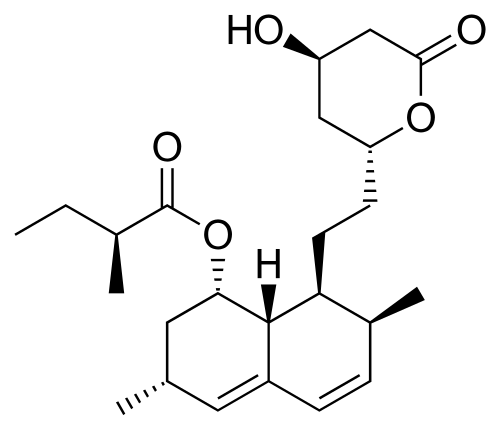
FDA approval of lovastatin, the first statin (HMG-CoA reductase inhibitor) (1987)
Framingham helped establish high cholesterol as a coronary risk, the target lovastatin was built to lower. The lovastatin entry shows how a mold compound found in 1973 became the first statin in 1987.
Read this moment
 Today on The Clinical Times
Florida dengue outbreak appears to be largest in continental U.S. in decades
Florida has reported more than 250 locally acquired dengue cases this year, with most in Hillsborough County, according to state health officials.
Read today’s top stories
All 526 moments in the history of medicine. This one is in chapter 6, Trials, scanners and rights
Connected moments
How this moment links to others in the history of medicine, and what you will find in each.
- Led to1967VA Cooperative Study of antihypertensive treatmentFramingham tied high blood pressure to heart attack and stroke, and the VA trial tested whether lowering it helped. That entry shows the first adequately powered placebo trial, with 27 serious complications on placebo against 2 on drugs.Read this moment
-
 Same disease or problem1978The Whitehall study of civil servantsBoth followed large groups to learn who develops coronary disease and why. Whitehall shows that the lowest grade of civil servants died of heart disease at 3.6 times the top rate, a gap risk factors only partly explained.Read this moment