Neurology & Psychiatry
1958
Imipramine, the first tricyclic antidepressant (Kuhn)
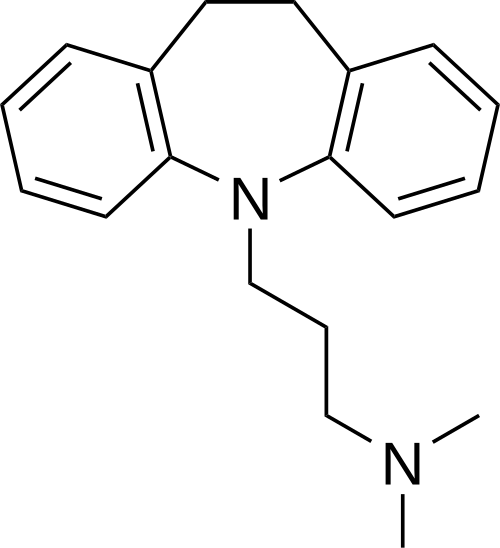
Imipramine, tested by Roland Kuhn on depressed patients from 1956, was the first tricyclic antidepressant; with the MAO inhibitor iproniazid it was one of the first two specific antidepressants, both introduced in 1957. Its action on monoamine reuptake anchored the monoamine theory of depression and the antidepressant classes that followed.
Key people
- Roland Kuhn
- Swiss psychiatrist who conducted the clinical trial and reported imipramine's antidepressant effects.
- Julius Axelrod
- Pharmacologist who elucidated catecholamine reuptake, explaining imipramine's mechanism.
Source
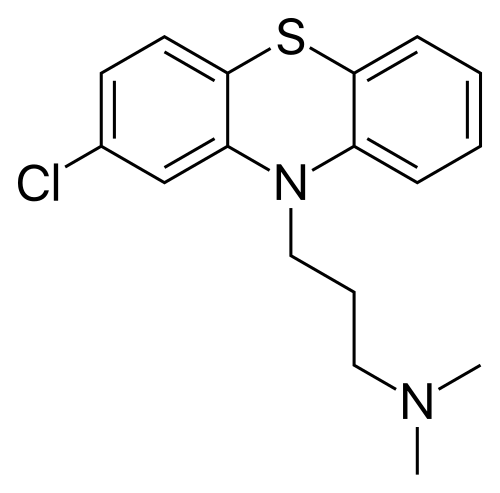
Psychiatry in the mid-1950s had almost nothing to offer patients with severe depression other than electroconvulsive therapy, barbiturate sedation, or admission to a long-term facility. Roland Kuhn, deputy medical director of the cantonal psychiatric clinic at Münsterlingen, near Lake Constance, had tested Geigy compounds before, and after chlorpromazine's success he asked the Swiss firm for new drugs of the same family to try in psychotic patients. In early 1956 he received G 22355, later named imipramine: a three-ring compound with the same side chain as chlorpromazine, made by Franz Häfliger and Walter Schindler in 1948.
Kuhn's initial results with schizophrenic patients were disappointing: imipramine did not suppress psychosis, and some patients became agitated. But three patients with depressive psychosis improved markedly within a few weeks, and on February 4, 1956, Kuhn wrote to Geigy that the drug might be an antidepressant. He gave it to 37 more depressed patients and presented the results from all 40 at the Second International Congress of Psychiatry in Zurich in September 1957, to an audience of about a dozen people; his report appeared in the Schweizerische Medizinische Wochenschrift that year. In the American Journal of Psychiatry in 1958 he described his experience with about 500 patients, reporting no serious side effects.
The mechanism was not known at the time of these clinical observations. Subsequent laboratory work by Julius Axelrod and others demonstrated that imipramine blocked the presynaptic reuptake of norepinephrine and serotonin, prolonging their dwell time in the synaptic cleft. That finding gave the monoamine hypothesis of depression its most direct clinical support: a drug that raised synaptic catecholamine and serotonin levels lifted mood in people with depressive illness. The hypothesis was not without critics, and it has been substantially revised and complicated since, but it organized psychopharmacological research for decades.
Geigy launched imipramine as Tofranil in Switzerland at the end of 1957 and in the rest of Europe in the spring of 1958, and the FDA approved it in 1959. The tricyclic class expanded quickly: amitriptyline, nortriptyline, desipramine, and clomipramine followed, each with a somewhat different receptor profile but the same core mechanism and a similar side-effect burden. That burden, which included significant anticholinergic effects (dry mouth, constipation, urinary retention, cognitive slowing) and cardiac conduction slowing, limited their use in elderly patients and made overdose particularly dangerous, since a tricyclic taken in excess could cause fatal arrhythmia.
Fluoxetine, the first selective serotonin reuptake inhibitor approved in the United States, received FDA approval in December 1987 and rapidly displaced the tricyclics as first-line antidepressants because of its far more favorable safety profile in overdose and its reduced anticholinergic burden. An earlier SSRI, zimelidine, had been sold in Europe for 16 months before cases of Guillain-Barré syndrome ended its use. Tricyclics did not disappear from practice; they kept a role in neuropathic pain, migraine prophylaxis, and treatment-resistant depression.
Keep exploring
 Read next · built on
Chlorpromazine in psychosis (Delay & Deniker) (1952)
Kuhn asked Geigy for chemical cousins of chlorpromazine and found that imipramine lifted depression instead. The chlorpromazine entry shows the first antipsychotic easing agitation and delusions in 1952 without heavy sedation.
Read this moment
 Today on The Clinical Times
Florida dengue outbreak appears to be largest in continental U.S. in decades
Florida has reported more than 250 locally acquired dengue cases this year, with most in Hillsborough County, according to state health officials.
Read today’s top stories
All 526 moments in the history of medicine. This one is in chapter 5, Cures and codes
Connected moments
How this moment links to others in the history of medicine, and what you will find in each.
-
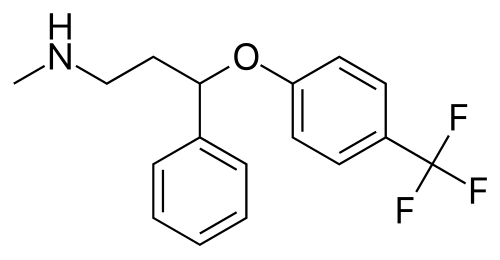 Led to1987Fluoxetine (Prozac) approval: first widely used SSRIImipramine's action on monoamine reuptake shaped the antidepressants that followed, and fluoxetine displaced the tricyclics. Its entry shows how a drug far safer in overdose made treating depression routine in primary care.Read this moment
-
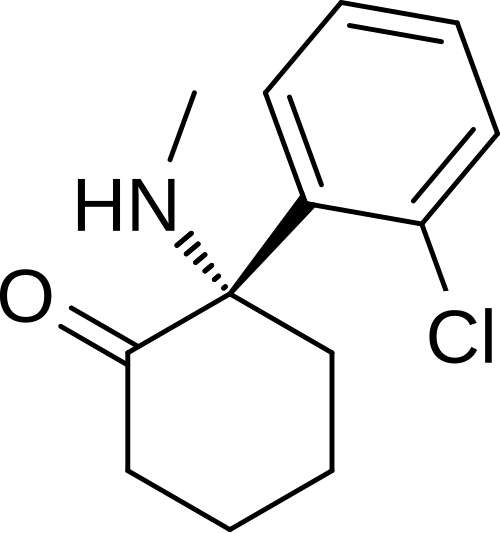 Same disease or problem2019Esketamine (Spravato) for treatment-resistant depressionEsketamine broke from the monoamine approach that imipramine anchored in the 1950s. Its entry shows the first antidepressant acting on the glutamate pathway, approved in 2019 for depression that standard drugs had failed.Read this moment