Endocrinology
2015
EMPA-REG OUTCOME
The first cardiovascular outcome trial of a glucose-lowering drug to show lower cardiovascular and all-cause death in type 2 diabetes, with a 38% cut in cardiovascular mortality. Hospitalization for heart failure fell by 35%.
Key people
- Bernard Zinman
- Principal investigator, led the EMPA-REG OUTCOME trial
- Silvio Inzucchi
- Senior author of the 2015 report; co-author of the 2016 renal analysis
- Christoph Wanner
- First author of the 2016 renal outcomes analysis
- Hans-Juergen Woerle
- Co-author of the 2015 report and the 2016 renal analysis
Source
After 2008, cardiovascular outcome trials of new diabetes drugs were designed mainly to show that the drugs did not raise cardiovascular risk. The 2008 FDA guidance requiring cardiovascular safety data for all new diabetes agents grew directly from the rosiglitazone episode, in which a widely used drug appeared to increase myocardial infarction risk. Drug makers responded by running large cardiovascular outcome trials, most of which showed neutral results. A neutral result for empagliflozin would have fit that pattern.
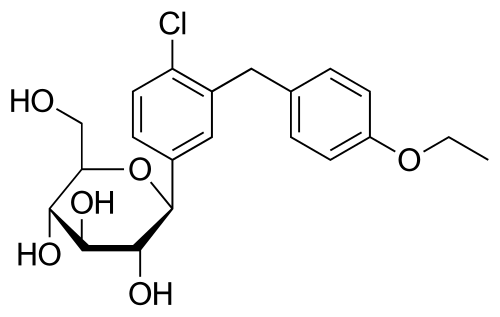
EMPA-REG OUTCOME enrolled 7,020 adults with type 2 diabetes and established cardiovascular disease across 42 countries, randomizing them to empagliflozin (10 mg or 25 mg) or placebo added to standard care. The primary composite endpoint was cardiovascular death, nonfatal myocardial infarction, or nonfatal stroke. Bernard Zinman of Mount Sinai Hospital in Toronto presented the results at the European Association for the Study of Diabetes meeting in Stockholm in September 2015, after a median observation time of 3.1 years. Empagliflozin cut the primary endpoint by 14%, cardiovascular mortality by 38%, and all-cause mortality by 32%; hospitalization for heart failure fell by 35%.
The magnitude of the mortality reduction surprised the field, partly because the HbA1c difference between the groups was modest. That mismatch suggested the benefit was not primarily glycemic. Debate over mechanism centered on the drug's osmotic diuretic effect, reduction in arterial stiffness, ketone body metabolism, and direct cardiac and renal effects. The renal analysis published in 2016, showing a 39% lower risk of new or worsening nephropathy (12.7% vs 18.8%), reinforced the view that SGLT2 inhibition was acting on hemodynamic and metabolic pathways beyond glucose disposal.
Rates of myocardial infarction and stroke did not differ significantly between the groups, which pointed away from slowed atherosclerosis and toward a hemodynamic or metabolic mechanism. Silvio Inzucchi was the report's senior author. Peer response ranged from enthusiasm to skepticism about whether the results could be generalized to lower-risk patients not yet carrying cardiovascular disease.
The clinical consequences arrived quickly. In the following years, SGLT2 inhibitors entered diabetes, cardiology and nephrology guidelines as preferred agents for patients with heart failure, chronic kidney disease, or established cardiovascular disease. Subsequent trials, CREDENCE for canagliflozin and DAPA-HF and DAPA-CKD for dapagliflozin, confirmed organ protection across the class, extending indications to patients without diabetes entirely. The SGLT2 inhibitor class is now listed in heart failure guidelines at the same level of evidence as beta-blockers and renin-angiotensin system agents.
Keep exploring
 Read next · led to
DAPA-HF (Dapagliflozin in heart failure with reduced ejection fraction) (2019)
EMPA-REG's drop in heart failure hospitalization led to trials of the same drug class in heart failure itself. DAPA-HF shows dapagliflozin helping patients with or without diabetes.
Read this moment
 Today on The Clinical Times
Florida dengue outbreak appears to be largest in continental U.S. in decades
Florida has reported more than 250 locally acquired dengue cases this year, with most in Hillsborough County, according to state health officials.
Read today’s top stories
All 526 moments in the history of medicine. This one is in chapter 7, Genes and pandemics
Connected moments
How this moment links to others in the history of medicine, and what you will find in each.
-
 Same disease or problem2016LEADERBoth were cardiovascular outcome trials that found a diabetes drug saving lives, not just proving it safe. The LEADER entry shows liraglutide cutting cardiovascular death by 22 percent.Read this moment
-
 Same disease or problem2008ACCORDACCORD showed pushing glucose lower could raise deaths, and EMPA-REG showed a glucose drug cutting deaths for reasons beyond glucose. The ACCORD entry shows its intensive arm halted early.Read this moment
-
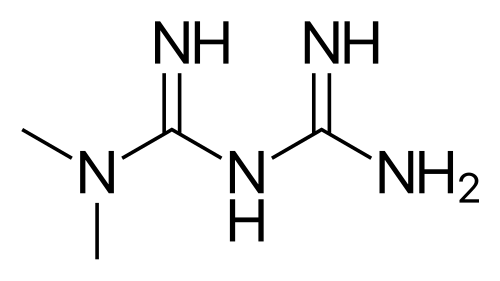
 Same disease or problem1998UK Prospective Diabetes Study (UKPDS 33)UKPDS found metformin cut diabetes deaths, and EMPA-REG was the first trial of a newer glucose drug to cut cardiovascular death. The UKPDS entry shows the benefits of tighter control in type 2 diabetes.Read this moment