Cardiology
2009
RE-LY (Dabigatran versus warfarin in atrial fibrillation)
The trial behind the first direct oral anticoagulant to reach routine use in atrial fibrillation. Dabigatran 150 mg beat warfarin for stroke prevention with less intracranial bleeding and no INR checks, opening the DOAC era before ROCKET-AF and ARISTOTLE.
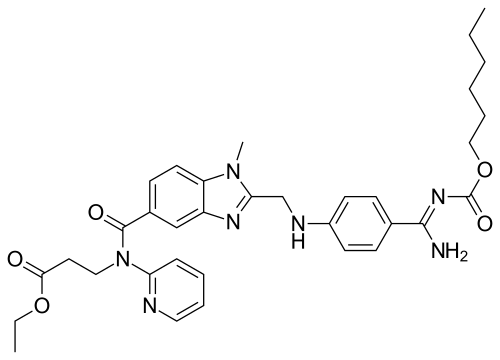
Key people
- Stuart Connolly
- Principal investigator; led RE-LY trial design and execution
- Michael Ezekowitz
- Co-investigator; contributed to trial design and conduct
- Salim Yusuf
- McMaster University; senior oversight of the RE-LY program
- Lars Wallentin
- Uppsala University; co-investigator and contributor to DOAC trial program
Source
Warfarin had been the standard anticoagulant for stroke prevention in atrial fibrillation since the late 1980s and early 1990s, when trials such as AFASAK and SPAF established its efficacy. Its clinical shortcomings were well known: a narrow therapeutic window, food and drug interactions, the need for regular INR monitoring, and a risk of intracranial hemorrhage that made physicians and patients reluctant to initiate or maintain it. An earlier oral direct thrombin inhibitor, ximelagatran, had been compared with warfarin in 3,410 patients in the SPORTIF III trial in 2003. By the late 2000s, dabigatran, another direct thrombin inhibitor, had been developed as an alternative that required no coagulation monitoring and could be given at a fixed dose.
RE-LY randomized 18,113 patients with atrial fibrillation and at least one additional stroke risk factor across 951 centers in 44 countries. Stuart Connolly of McMaster University led the trial design and execution. The study used an unusual design: the two dabigatran doses were blinded, while warfarin was open-label, maintained at an INR of 2 to 3. Michael Ezekowitz contributed to the trial's design and conduct.
The 150 mg twice-daily dose of dabigatran reduced the combined outcome of stroke and systemic embolism from 1.69% per year on warfarin to 1.11% per year, a relative risk reduction of approximately 34%, with similar rates of major bleeding overall. Hemorrhagic stroke occurred at 0.10% per year with the 150 mg dose and 0.38% per year with warfarin. The 110 mg dose was non-inferior to warfarin on stroke prevention and produced less major bleeding, offering an option for patients at higher bleeding risk.
Publication in the New England Journal of Medicine in 2009 was followed quickly by FDA approval of dabigatran for stroke prevention in nonvalvular atrial fibrillation on October 19, 2010. ROCKET-AF reported rivaroxaban data in 2011 and ARISTOTLE reported apixaban data in 2011, both confirming the pattern of non-inferiority or superiority on stroke prevention with better intracranial hemorrhage profiles than warfarin. Together, the three trials made direct oral anticoagulants an established alternative to warfarin for most patients with atrial fibrillation who needed anticoagulation.
The practical consequence for outpatient medicine was that patients who previously went without anticoagulation because of the monitoring burden, or who had poorly controlled INRs, could be offered a fixed-dose regimen without routine laboratory follow-up. Dabigatran later drew controversy over bleeding and over whether some patients would benefit from measuring drug levels, which fixed dosing had been promoted as making unnecessary.
Keep exploring
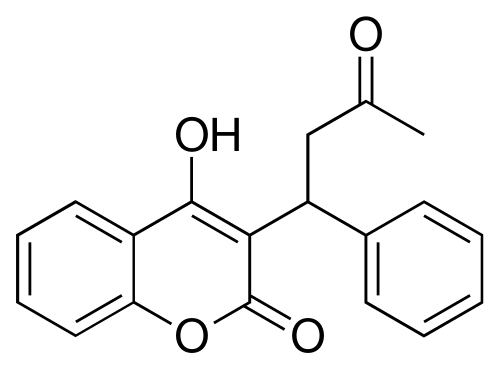 Read next · built on
Warfarin introduced for clinical anticoagulation (1954)
RE-LY tested dabigatran against warfarin, the standard oral anticoagulant for more than five decades. The warfarin entry shows how it reached patients in 1954 and why its monitoring burden invited a replacement.
Read this moment
 Today on The Clinical Times
Florida dengue outbreak appears to be largest in continental U.S. in decades
Florida has reported more than 250 locally acquired dengue cases this year, with most in Hillsborough County, according to state health officials.
Read today’s top stories
All 526 moments in the history of medicine. This one is in chapter 7, Genes and pandemics
Connected moments
How this moment links to others in the history of medicine, and what you will find in each.
-
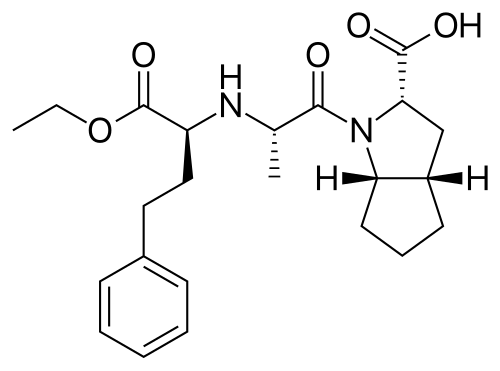 Same person2000HOPE (Heart Outcomes Prevention Evaluation)Salim Yusuf of McMaster was part of both trials, which came from the same Canadian research group. The HOPE entry shows ramipril protecting high-risk patients without heart failure.Read this moment
-
 Same disease or problem1995NINDS rt-PA Stroke TrialRE-LY aimed to prevent strokes in atrial fibrillation, and the NINDS trial treated strokes once they struck. The NINDS entry shows clot dissolving t-PA reducing disability when given within three hours.Read this moment
-
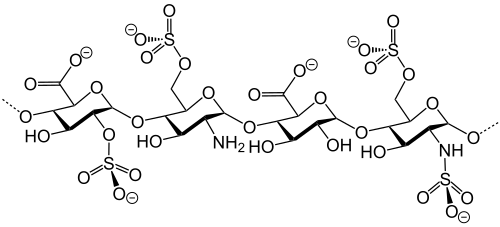 Same disease or problem1937Heparin as an injectable anticoagulantBoth gave doctors a way to stop dangerous clotting, heparin by injection in 1937 and dabigatran as a fixed-dose pill. The heparin entry shows how a purified anticoagulant made bypass and dialysis possible.Read this moment