Infectious Disease
1997
ACTG 320: Triple-Drug Combination Antiretroviral Therapy
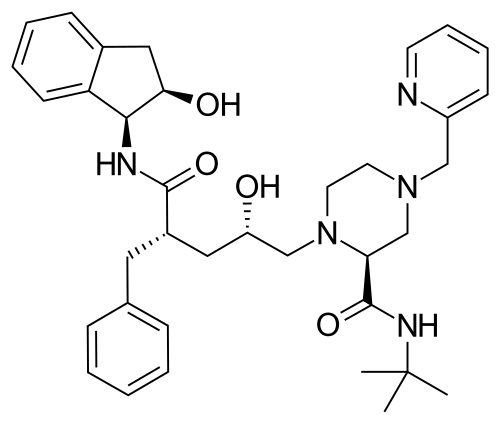
In 1,156 patients with advanced HIV, adding indinavir to two nucleosides cut progression to AIDS or death from 11% to 6% and mortality from 3.1% to 1.4%, helping make three-drug therapy the standard of care.
Key people
- Scott Hammer
- First author of the 1997 ACTG 320 report
- Michael Hughes
- Harvard biostatistician and co-author of the ACTG 320 report
- Margaret Fischl
- University of Miami infectious diseases physician and senior author of the ACTG 320 report
- Kathleen Squires
- University of Alabama at Birmingham HIV researcher and second author of the ACTG 320 report
Source
The Vancouver conference in 1996 had generated conviction based largely on open-label cohort data and viral kinetics. Convincing as those results were to many virologists, they did not constitute a randomized trial. Clinicians who wanted to prescribe triple therapy to every patient with advanced HIV needed controlled evidence, and the ACTG 320 trial was designed to provide it.
AIDS Clinical Trials Group Protocol 320 enrolled 1,156 adults who had taken zidovudine but never lamivudine or a protease inhibitor, all with CD4 counts of 200 cells per cubic millimeter or fewer, a group at high near-term risk of progression. Participants were randomized to zidovudine (or stavudine) and lamivudine with or without indinavir, a protease inhibitor the FDA had approved in March 1996. Patients were stratified by CD4 count, 50 or fewer versus 51 to 200, and the primary endpoint was time to AIDS or death. Scott Hammer was the first author of the report, and Margaret Fischl of the University of Miami was its senior author.
The results appeared in the New England Journal of Medicine on September 11, 1997. In the indinavir arm, 6 percent of patients had reached the primary endpoint versus 11 percent in the two-nucleoside arm, a hazard ratio of 0.50. Mortality was 1.4 percent versus 3.1 percent, a hazard ratio of 0.43. Both differences were statistically significant. The effect was similar in both CD4 strata, and CD4 counts and plasma HIV RNA moved in step with the clinical results.
NIAID describes ACTG 320 as one of the studies that established the efficacy of triple-drug therapy. Adding a drug from a new class to a two-drug backbone lowered the death rate, not only viral load, and the trial showed that patients changing treatment did better when two new drugs were added than when one was.
Treatment advice moved quickly. In June 1997 the International AIDS Society-USA panel, whose members included Hammer and Fischl, wrote that new data gave a stronger rationale for starting more aggressive therapy earlier, and in April 1998 treatment guidelines from a Department of Health and Human Services panel were published in the CDC's MMWR. The CD4 threshold for starting treatment then moved up and down for years; US guidelines dropped it in 2013, and randomized trials settled the question in 2015.
Keep exploring
 Read next · built on
Highly Active Antiretroviral Therapy (HAART) and the Vancouver protease-inhibitor combination era (1996)
Vancouver built conviction on cohort data and viral counts, and ACTG 320 supplied the randomized proof. The HAART entry shows three-drug combinations pushing HIV below detection and AIDS deaths falling.
Read this moment
 Today on The Clinical Times
Florida dengue outbreak appears to be largest in continental U.S. in decades
Florida has reported more than 250 locally acquired dengue cases this year, with most in Hillsborough County, according to state health officials.
Read today’s top stories
All 526 moments in the history of medicine. This one is in chapter 6, Trials, scanners and rights
Connected moments
How this moment links to others in the history of medicine, and what you will find in each.
-
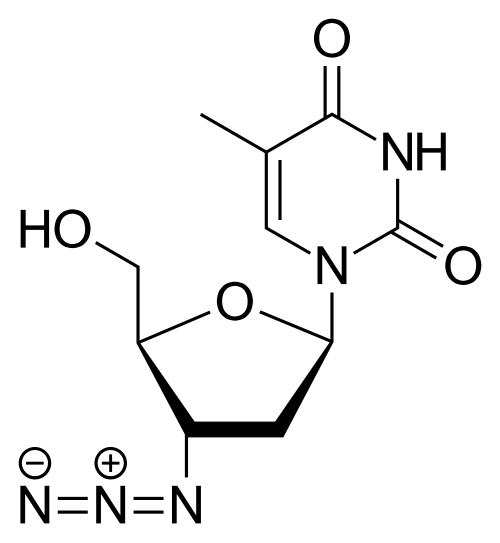 Same person1987AZT (Zidovudine) Trial for AIDSMargaret Fischl, senior author of ACTG 320, had also worked on the first AZT trial a decade earlier. The AZT entry shows the drug that began HIV treatment, and why it failed on its own.Read this moment
-
 Same disease or problem2011HPTN 052: Antiretroviral Therapy as HIV PreventionAfter ACTG 320, doctors argued for years about when to start treatment, and HPTN 052 showed early treatment also protects partners. It shows HIV transmission cut by 96 percent.Read this moment