Infectious Disease
1987
AZT (Zidovudine) Trial for AIDS
The first drug shown to extend survival in AIDS. In 282 patients, AZT cut deaths to 1 versus 19 on placebo over the trial period, which was halted early. The FDA approved it on March 19, 1987, as the first medication for AIDS.
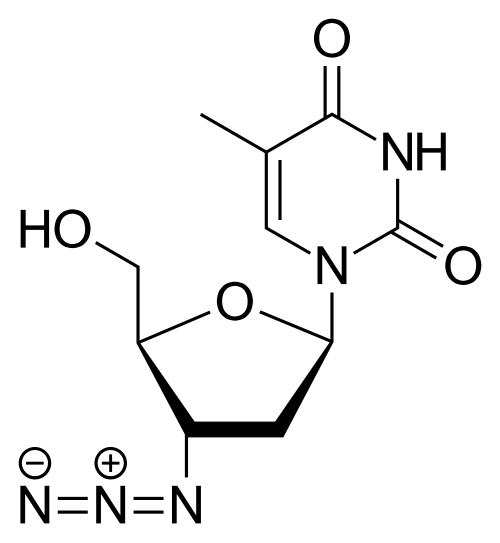
Key people
- Samuel Broder
- NCI scientist, later the institute's director, who championed zidovudine's clinical development
- Jerome Horwitz
- Detroit Institute for Cancer Research chemist who first synthesized AZT in 1964
- Phillip Furman
- Burroughs Wellcome researcher who established AZT's anti-HIV activity
- Margaret Fischl
- University of Miami investigator and first author of the 1987 report of the placebo-controlled AZT trial
Source
By 1986 AIDS was spreading fast in the United States, where reported cases would reach 100,000 by 1989, and there was no approved treatment. Once AIDS developed, the immune destruction caused by HIV led to death. The Food and Drug Administration's standard drug approval pathway required years of phased trials, a timeline that was incompatible with the urgency of a uniformly fatal epidemic with no therapeutic options. Patient advocacy groups were demanding access to experimental drugs, and pressure on the FDA and the National Cancer Institute to move faster was intense.
Zidovudine had first been synthesized by Jerome Horwitz at the Detroit Institute for Cancer Research in 1964 as a potential cancer treatment; it failed in that application and was shelved. In 1985 Hiroaki Mitsuya and Samuel Broder at the National Cancer Institute, with Phillip Furman and colleagues at Burroughs Wellcome and researchers at Duke, reported that it inhibited HIV reverse transcriptase and blocked the virus in cell culture. Broder pushed the compound quickly through early safety studies. The double-blind, placebo-controlled trial enrolled 282 patients with AIDS, shown by Pneumocystis pneumonia, or advanced AIDS-related complex; 145 received 250 mg of AZT every four hours and 137 received placebo, for a planned 24 weeks.
An interim safety monitoring board analysis halted the trial early when it found 19 deaths among placebo recipients against 1 among those receiving AZT. By then 27 patients had completed 24 weeks, 152 had completed 16 weeks and the rest at least 8 weeks. Opportunistic infections developed in 45 placebo recipients and 24 AZT recipients. The FDA gave the application priority review and approved zidovudine, sold as Retrovir, on March 19, 1987. The full clinical trial data were published in the New England Journal of Medicine in 1987.
The early benefits were real but incomplete. AZT reduced opportunistic infections and extended survival in patients with advanced disease. In the trial itself, CD4 counts in patients with AIDS rose but fell back to pretreatment values after 12 weeks, and as resistant virus emerged under single-drug treatment, patients who had responded went on to progress. The failure of monotherapy drove the research agenda toward combination antiretroviral therapy, ultimately yielding the triple-drug regimens that suppressed viral replication durably when introduced in the mid-1990s. Zidovudine remained a component of many of those combinations.
Pressure on the FDA grew. In 1987 it issued regulations expanding access to promising unapproved drugs, and in 1988, eight days after more than 1,000 ACT UP members and supporters shut down its offices in Rockville, Maryland, it announced rules to speed approvals. In 1992 it created accelerated approval, which lets drugs for serious conditions with unmet needs be approved on a surrogate endpoint. Many later antiretrovirals and cancer drugs reached patients through that pathway.
Keep exploring
 Read next · built on
First report of AIDS (Pneumocystis pneumonia cluster) (1981)
The trial enrolled patients whose AIDS had shown itself as Pneumocystis pneumonia, the illness of the first 1981 report. That entry shows five young men in Los Angeles and the epidemic that followed.
Read this moment
 Today on The Clinical Times
Florida dengue outbreak appears to be largest in continental U.S. in decades
Florida has reported more than 250 locally acquired dengue cases this year, with most in Hillsborough County, according to state health officials.
Read today’s top stories
All 526 moments in the history of medicine. This one is in chapter 6, Trials, scanners and rights
Connected moments
How this moment links to others in the history of medicine, and what you will find in each.
-
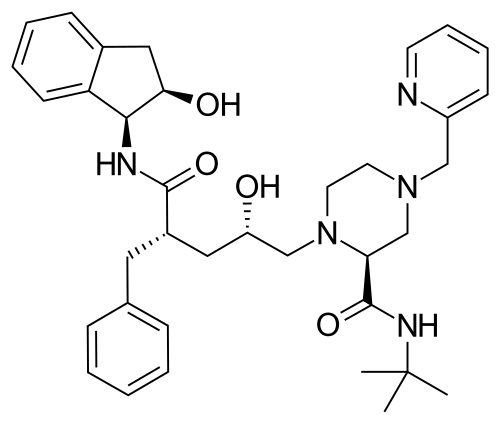 Led to1997ACTG 320: Triple-Drug Combination Antiretroviral TherapyAZT alone failed as resistant virus emerged, which drove research toward combination therapy. ACTG 320 shows adding a third drug halving progression to AIDS or death.Read this moment
-
 Same disease or problem1988ACT UP's protest at the FDAPressure on the FDA to move faster on AIDS drugs grew after AZT, and activists shut down its offices a year later. The ACT UP entry shows the new rules that followed within days.Read this moment
- Led to1994ACTG 076 perinatal HIV prevention trialZidovudine later found a second use in preventing HIV from passing from mother to baby. ACTG 076 shows it cutting transmission from 25.5 to 8.3 percent.Read this moment