Infectious Disease
1996
Highly Active Antiretroviral Therapy (HAART) and the Vancouver protease-inhibitor combination era
At the 1996 Vancouver AIDS conference, researchers reported three-drug combinations that could suppress HIV to minimal levels. In 1997 the ACTG 320 trial showed that adding indinavir to two nucleosides halved progression to AIDS or death.
Key people
- David Ho
- Aaron Diamond AIDS Research Center scientist who argued in 1995 for treating HIV early and hard
- Julio Montaner
- BC Centre for Excellence in HIV/AIDS physician who led the INCAS triple-therapy trial
- Scott Hammer
- First author of the 1997 ACTG 320 report
- Martin Markowitz
- Aaron Diamond researcher and co-author of the 1995 and 1996 viral dynamics studies
Source
Through the early 1990s, HIV treatment meant nucleoside reverse transcriptase inhibitors given alone or in pairs, and the benefit of two-drug therapy, though greater than that of one drug, did not last. On a single drug, resistance appeared soon, and most patients went on to develop AIDS illnesses again. The approval of saquinavir in December 1995 introduced the protease inhibitor class, but how aggressively to deploy it and in what combinations remained unsettled.
Three-drug combinations were the focus of the XI International Conference on AIDS, held in Vancouver in 1996; in many patients they pushed the amount of HIV in the blood below the limit of detection. David Ho of the Aaron Diamond AIDS Research Center in New York had called for aggressive early treatment in a 1995 editorial titled Time to Hit HIV, Early and Hard. A 1996 analysis by his group and theorists at Los Alamos estimated that an infected person produced about 10 billion virus particles a day. Julio Montaner of the Vancouver-based BC Centre for Excellence in HIV/AIDS led the INCAS trial, in which a triple regimen containing a non-nucleoside reverse transcriptase inhibitor suppressed viral load to undetectable levels. The concept that came out of Vancouver was soon called highly active antiretroviral therapy.
The effect showed up quickly in national figures. In 1996 the number of new AIDS diagnoses in the United States fell for the first time in the epidemic, and AIDS stopped being the leading cause of death for all Americans aged 25 to 44. In 1997, largely because of the new treatment, US AIDS deaths fell by 47 percent from the year before.
The ACTG 320 trial, published in the New England Journal of Medicine in September 1997, provided the controlled evidence. It enrolled 1,156 zidovudine-treated patients with CD4 counts of 200 or fewer and randomized them to indinavir plus two nucleosides or the two nucleosides alone; Scott Hammer was the first author of the report. Progression to AIDS or death fell from 11 percent to 6 percent, and mortality from 3.1 percent to 1.4 percent. The trial also showed that patients changing therapy did better when two new drugs were added than when one was.
The early regimens were hard to take, with burdensome side effects and complicated schedules. In a 2000 study that tracked 81 patients' protease inhibitor doses electronically, treatment failed virologically in 22 percent of those who took at least 95 percent of doses, 61 percent of those who took 80 to 94.9 percent, and 80 percent of the rest. Combination tablets cut the pill count, and in July 2006 the FDA approved Atripla, which put efavirenz, emtricitabine and tenofovir in a single tablet.
Keep exploring
 Read next · built on
AZT (Zidovudine) Trial for AIDS (1987)
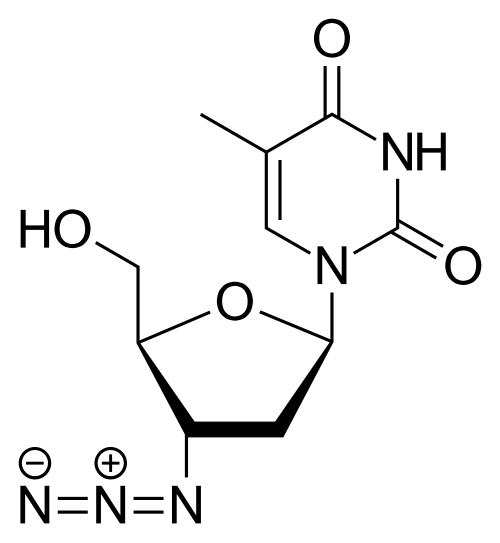
AZT alone failed as resistance appeared, and combinations of three drugs finally held HIV down. The AZT entry shows the first drug proven to extend survival in AIDS.
Read this moment
 Today on The Clinical Times
Florida dengue outbreak appears to be largest in continental U.S. in decades
Florida has reported more than 250 locally acquired dengue cases this year, with most in Hillsborough County, according to state health officials.
Read today’s top stories
All 526 moments in the history of medicine. This one is in chapter 6, Trials, scanners and rights
Connected moments
How this moment links to others in the history of medicine, and what you will find in each.
-
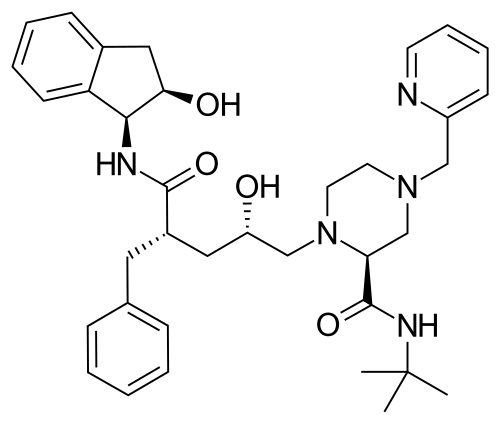 Same person1997ACTG 320: Triple-Drug Combination Antiretroviral TherapyScott Hammer led ACTG 320, the controlled trial that proved what Vancouver had shown. That entry shows adding indinavir halving progression to AIDS or death.Read this moment
-
 Same person2011HPTN 052: Antiretroviral Therapy as HIV PreventionJulio Montaner, who led a key Vancouver trial, had also modeled treatment as prevention before HPTN 052 proved it. That entry shows early treatment cutting HIV transmission between partners by 96 percent.Read this moment
-
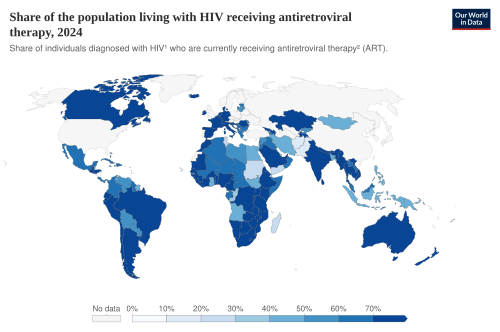
 Same disease or problem2003President's Emergency Plan for AIDS Relief (PEPFAR)Combination therapy turned HIV into a treatable disease, and PEPFAR paid to bring that treatment to millions abroad. Its entry shows 20.6 million people receiving HIV treatment by 2024.Read this moment