Cardiology
1987
CONSENSUS (Cooperative North Scandinavian Enalapril Survival Study)
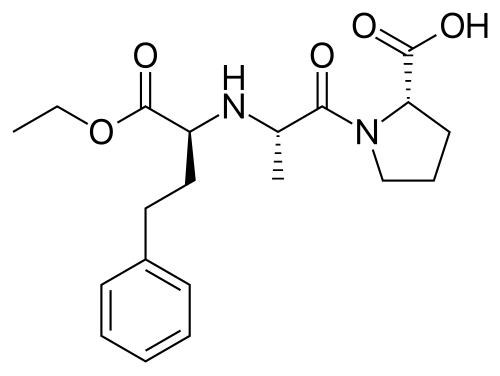
The first trial to show that an ACE inhibitor cuts deaths in heart failure: among 253 patients with NYHA class IV disease, enalapril lowered six-month mortality from 44% to 26%. Blocking the renin-angiotensin system became part of standard treatment.
Key people
- John Kjekshus
- Lead investigator of the CONSENSUS trial, Norwegian cardiologist
- Karl Swedberg
- Co-investigator; subsequent leader in European heart failure research
Source
By the mid-1980s, heart failure management had reached something of a ceiling. Diuretics and digoxin controlled fluid retention and symptoms, but neither agent had been shown to extend survival. The neurohumoral hypothesis, which held that activation of the renin-angiotensin-aldosterone system was driving progressive ventricular dysfunction, had theoretical support but no large trial had tested whether blocking it altered mortality. The patients most likely to benefit were also the most precarious: in CONSENSUS, 44 percent of those with NYHA class IV disease on placebo died within six months.
CONSENSUS enrolled 253 patients with NYHA class IV heart failure at Scandinavian centers and randomized them, double-blind, to enalapril (127 patients, 2.5 to 40 mg a day) or placebo (126), on top of conventional treatment that included other vasodilators. Led by John Kjekshus and co-investigator Karl Swedberg, the trial was designed to detect a survival signal in the most severe heart failure population then studied. At six months, mortality was 44% in the placebo group and 26% in the enalapril group, a 40 percent reduction; at one year it was 31 percent lower. The difference was large enough that the trial's safety committee stopped it early, judging continued placebo assignment unethical.
The results, published in the New England Journal of Medicine in June 1987, showed that the whole reduction came from fewer deaths from progressive heart failure, with no difference in sudden cardiac death. Hypotension led to withdrawal in seven enalapril patients and none on placebo, and became less frequent once the starting dose was cut to 2.5 mg in high-risk patients. The trial was small and confined to the sickest patients. The SOLVD Treatment Trial of 1991 enrolled 2,569 patients with ejection fractions of 35% or less, about 90 percent of them in NYHA classes II and III, and found a 16 percent reduction in deaths with enalapril.
Neurohormonal blockade, the approach CONSENSUS supported, guided heart failure drug treatment over the following three decades. Beta-blockers, which had long been considered contraindicated in heart failure, were subsequently tested and shown to further reduce mortality; spironolactone and eplerenone extended blockade to the mineralocorticoid pathway. Each of these drug classes demonstrated incremental mortality reductions that were layered onto the ACE inhibitor foundation established by CONSENSUS.
Today, the guideline-directed medical therapy for heart failure with reduced ejection fraction includes an ACE inhibitor or ARNI, a beta-blocker, a mineralocorticoid antagonist, and an SGLT2 inhibitor. CONSENSUS did not establish that entire regimen, but it provided the first mortality evidence for blocking the renin-angiotensin system in heart failure. Its patients were followed for an average of 188 days, and by the end of the study there had been 68 deaths on placebo and 50 on enalapril.
Keep exploring
 Read next · built on
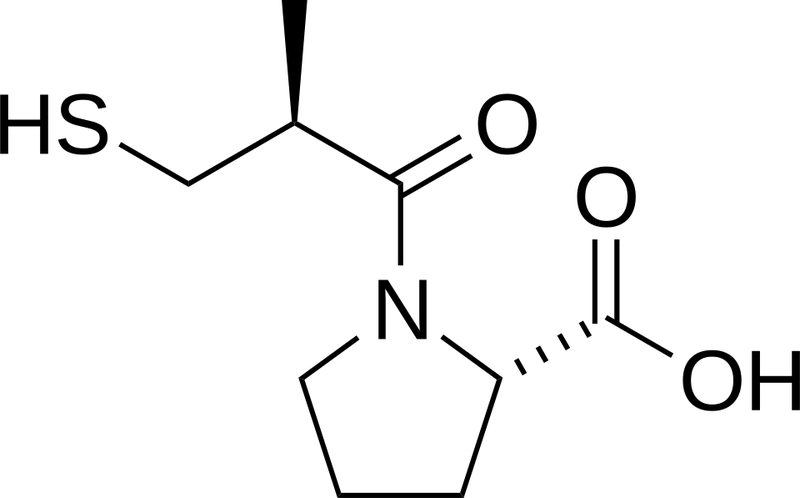
Captopril, the first ACE inhibitor (1981)
CONSENSUS tested enalapril from the ACE inhibitor class that captopril opened in 1981. The captopril entry shows how snake venom and a model of the enzyme led to the first oral ACE inhibitor.
Read this moment
 Today on The Clinical Times
Florida dengue outbreak appears to be largest in continental U.S. in decades
Florida has reported more than 250 locally acquired dengue cases this year, with most in Hillsborough County, according to state health officials.
Read today’s top stories
All 526 moments in the history of medicine. This one is in chapter 6, Trials, scanners and rights
Connected moments
How this moment links to others in the history of medicine, and what you will find in each.
-
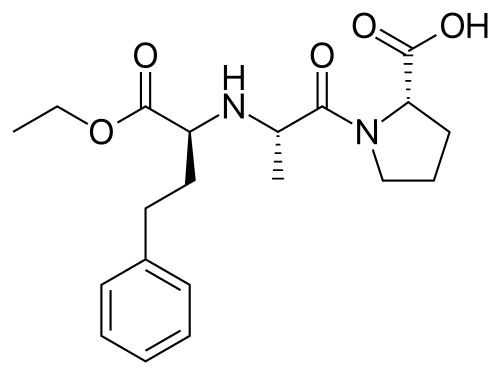 Led to1991SOLVD Treatment TrialCONSENSUS proved the benefit only in the sickest patients, and SOLVD extended it to milder heart failure. The SOLVD entry shows enalapril cutting deaths by 16 percent in 2,569 patients.Read this moment
-
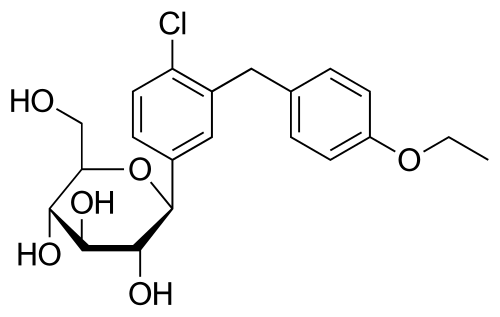 Same disease or problem2019DAPA-HF (Dapagliflozin in heart failure with reduced ejection fraction)CONSENSUS laid the ACE inhibitor foundation of heart failure treatment, and SGLT2 inhibitors were later added on top of it. DAPA-HF shows dapagliflozin cutting worsening heart failure or cardiovascular death.Read this moment
-
 Same person19944S (Scandinavian Simvastatin Survival Study)John Kjekshus, who led CONSENSUS, was also an investigator in the Scandinavian statin trial. The 4S entry shows simvastatin cutting deaths by 30 percent in coronary patients.Read this moment