Public Health
1968
Oral Rehydration Therapy for cholera and diarrheal disease
Nalin and Cash showed an oral glucose-salt drink cut intravenous fluid needs by about 80 percent in cholera patients, since glucose pulls sodium and water across the gut. The cheap therapy now treats diarrheal dehydration worldwide.

Key people
- David Nalin
- Physician who co-led the Dhaka trial demonstrating oral rehydration's clinical efficacy.
- Richard Cash
- Co-investigator on the 1968 cholera oral rehydration trial in Bangladesh.
- Norbert Hirschhorn
- Researcher who contributed parallel ORT work in cholera patients in the same period.
- Robert Phillips
- Physiologist whose earlier glucose-sodium absorption research provided the mechanistic basis for ORT.
Source
Cholera killed by dehydration, and before oral rehydration therapy, the only effective treatment was intravenous fluid replacement. In epidemic conditions in South and Southeast Asia, Africa, and Latin America, that constraint was lethal: IV fluids required sterile equipment, trained staff, and a functioning supply chain, none of which reliably existed where cholera killed the most people. Case fatality rates in untreated or poorly resourced settings routinely exceeded 20 to 30 percent.
The scientific basis for a different approach had been accumulating through the 1960s. Researchers including Robert Phillips had shown that glucose administration accelerated sodium absorption in the small intestine, and work at the Cholera Research Laboratory in Dhaka was clarifying the mechanism: cholera toxin causes massive secretion of sodium and water into the gut lumen by constitutively activating adenylate cyclase in enterocytes, but it does not disable the glucose-sodium cotransporter on the brush border. That transporter could still pull sodium, and water with it, across the epithelium if glucose was present in the lumen.
David Nalin and Richard Cash, working at the Cholera Research Laboratory in Dhaka in 1968, conducted a controlled trial that put this physiology directly to clinical test. They gave adult cholera patients an oral glucose-electrolyte solution and measured IV fluid requirements against controls. The oral solution cut IV fluid needs by approximately 80 percent. Patients who would otherwise have required continuous intravenous infusion were kept in fluid balance with a drink that could be prepared from sugar, salt, and clean water.
The simplicity of the solution was not incidental to its impact. Norbert Hirschhorn and colleagues working in parallel with cholera patients in the same period contributed supporting evidence, and the global health implications became clear quickly. Cholera struck hardest in places where hospitals were overwhelmed or absent. A therapy that community health workers could mix and administer without needles or electricity was a qualitatively different tool from anything previously available.
WHO and UNICEF standardized an oral rehydration salt formulation in 1975, and mass production and distribution followed over the next two decades. The WHO later introduced a reduced-osmolarity formulation in 2002 after trials showed it further reduced stool output and the need for supplemental IV fluids. A 1978 Lancet editorial called the discovery behind oral rehydration therapy potentially the most important medical advance of the century, and later estimates credited the therapy with preventing millions of child deaths a year from all-cause diarrheal disease, not cholera alone.
Keep exploring
 Read next · same disease or problem
Latta's saline injections for cholera (1832)
Both replaced the water and salt cholera drains from the body, Latta through the veins and ORT by mouth. Latta's entry shows warm salt water injected into collapsed patients in 1832, and several reviving.
Read this moment
 Today on The Clinical Times
Florida dengue outbreak appears to be largest in continental U.S. in decades
Florida has reported more than 250 locally acquired dengue cases this year, with most in Hillsborough County, according to state health officials.
Read today’s top stories
All 526 moments in the history of medicine. This one is in chapter 6, Trials, scanners and rights
Connected moments
How this moment links to others in the history of medicine, and what you will find in each.
-
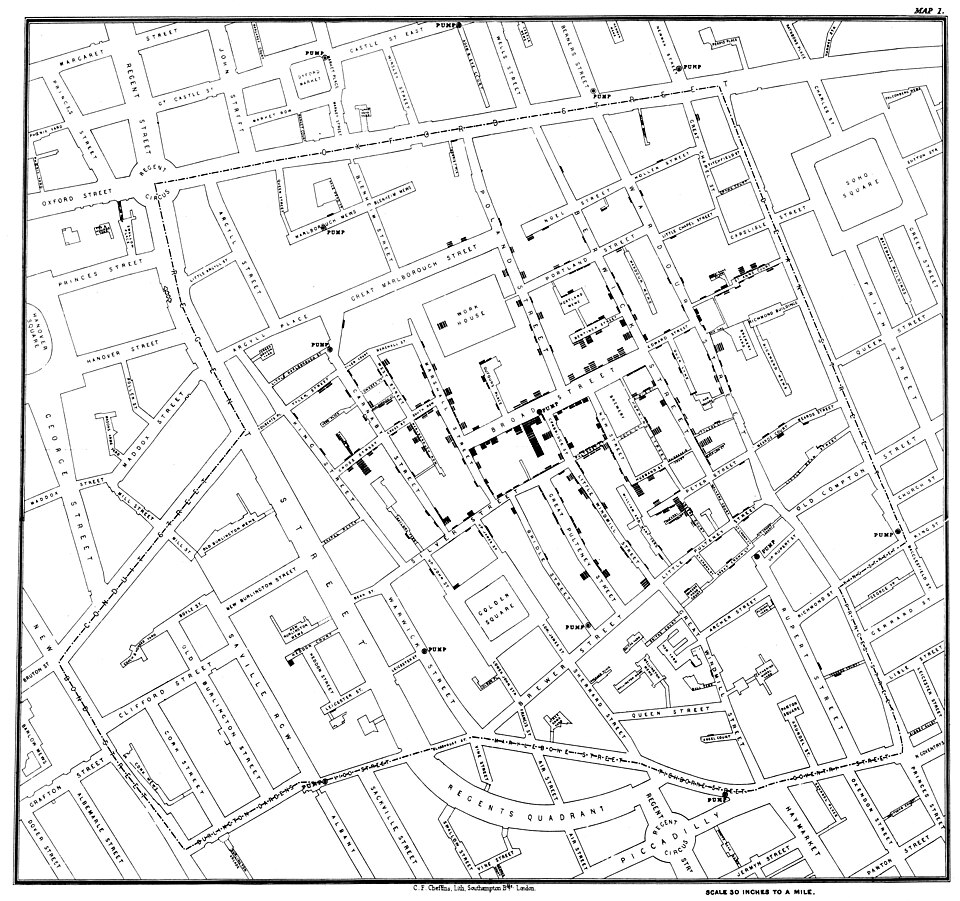 Same disease or problem1854John Snow and the Broad Street PumpSnow found how cholera spreads, and ORT gave a cheap way to survive it. Snow's entry shows the Broad Street pump investigation that tied cholera to drinking water.Read this moment
-
 Same disease or problem1883Koch's identification of the cholera bacillusKoch found the germ behind cholera, and ORT turned its deadly dehydration into something a drink could treat. Koch's entry shows the comma-shaped bacillus he found in Egypt and India.Read this moment