Surgery & Anesthesia
1966
National Halothane Study
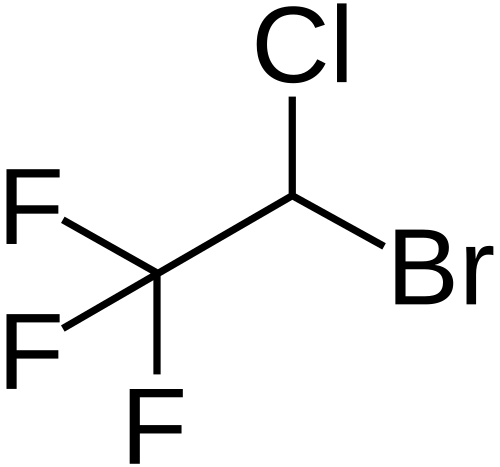
Prompted by case reports of liver death after halothane, this review of more than 800,000 anesthetics in 34 hospitals found massive hepatic necrosis rare and mostly explained by other causes, and set a model for comparing surgical outcomes across hospitals.
Key people
- John Bunker
- Anesthesiologist who chaired the National Halothane Study committee
- Lincoln Moses
- Biostatistician who led the study's analytic design at Stanford
Source
Halothane reached clinical practice in 1956 and was rapidly adopted because it was nonflammable, potent, and smoother to administer than the ether and cyclopropane it replaced. Within a few years, case reports began appearing of fatal hepatic necrosis in patients who had received it, some after a single exposure but more often after repeat anesthetics. Anesthesiologists disagreed over whether halothane caused the damage or whether hypotension, surgical trauma, or coincident disease explained it. No single institution had enough cases to answer the question, and there was no infrastructure for pooling data across hospitals.
The National Halothane Study was organized to provide that infrastructure. Under the leadership of John Bunker and with analytic direction from Lincoln Moses, a biostatistician at Stanford, a subcommittee of the National Academy of Sciences assembled postoperative records from 34 hospitals covering more than 800,000 anesthetics. It was among the largest retrospective outcome studies conducted in surgery or anesthesia to that point, and its summary appeared in JAMA in 1966.
The study found that massive hepatic necrosis was rare and, overall, no more common after halothane than after other anesthetics; most cases had other apparent causes. But among the few cases of acute hepatic necrosis with no aggravating cause, halothane was more likely to have been the anesthetic used, which is why the JAMA summary spoke of a possible association. To compare death rates fairly, the analysts adjusted for procedure, age, and preoperative physical status.
The result quieted the immediate alarm, but it did not close the case. In 1968 the Fulminant Hepatitis Group reported 150 cases from 73 centers: 24 percent of the patients had received halothane before the illness, and 77 percent of those had had more than one exposure. Granulomas and eosinophilia in some patients led to the proposal of a hypersensitivity mechanism, though fully recognizable hepatic necrosis after halothane remained very rare. Halothane continued in clinical use for decades, especially in pediatric anesthesia, but was eventually displaced by newer volatile agents with less hepatic metabolism.
The study's most lasting contribution came from its methods. After adjustment for procedure, age, and physical status, death rates still varied considerably among the 34 hospitals, a finding that helped start research on differences in hospital outcomes. In 1974 the Stanford Center for Health Care Research extended that kind of comparison to 1,224 hospitals.
Keep exploring
 Read next · same disease or problem
The Ether Demonstration ("Ether Day") (1846)
Halothane replaced ether as a smoother, nonflammable anesthetic, and then raised its own safety fears. The ether entry shows the 1846 Boston demonstration that began surgical anesthesia.
Read this moment
 Today on The Clinical Times
Florida dengue outbreak appears to be largest in continental U.S. in decades
Florida has reported more than 250 locally acquired dengue cases this year, with most in Hillsborough County, according to state health officials.
Read today’s top stories
All 526 moments in the history of medicine. This one is in chapter 6, Trials, scanners and rights
Connected moments
How this moment links to others in the history of medicine, and what you will find in each.
- Same disease or problem1999To Err Is HumanThe halothane study found death rates differing among hospitals, starting research on hospital outcomes and harm. To Err Is Human shows estimates that medical errors killed up to 98,000 Americans a year.Read this moment
-
 Same disease or problem1962Charnley low-friction arthroplastyBoth raised the question of whether results hold up across ordinary hospitals. Charnley's entry shows the low friction hip replacement and a study finding 83 percent of implants still in place after 25 years.Read this moment