Genetics & Molecular
2017
Voretigene Neparvovec (Luxturna): First FDA-Approved In Vivo Gene Therapy for an Inherited Disease
First gene therapy injected directly into the body to win FDA approval, on December 19, 2017. A single subretinal dose of a working RPE65 gene improved low-light navigation in patients with biallelic RPE65 retinal dystrophy.
Key people
- Albert Maguire
- Surgeon who performed subretinal injections in the phase 3 trial
- Jean Bennett
- Co-developer of RPE65 gene therapy at the University of Pennsylvania
- Katherine High
- Founded Spark Therapeutics; led commercial development of Luxturna
- Samuel Jacobson
- Retinal specialist; early collaborator on RPE65 natural history studies
Source
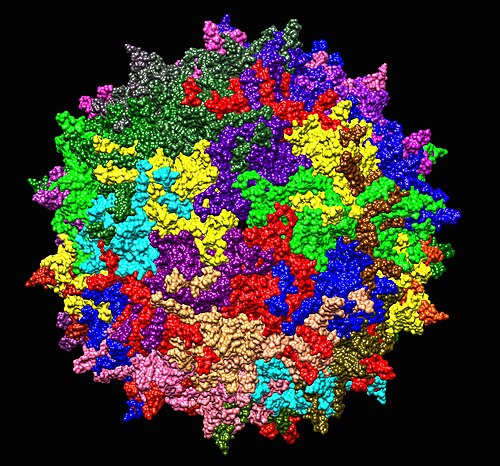
Before Luxturna, patients with biallelic RPE65 mutation-associated retinal dystrophy had no treatment to slow their progressive visual loss. The condition, caused by a deficient or absent RPE65 enzyme critical for the visual cycle, typically produces severe night blindness in childhood and leads to legal or complete blindness by adulthood. Retinal gene therapy research had been underway for years, with early-phase trials at the University of Pennsylvania showing that a functional RPE65 gene could be delivered to retinal pigment epithelium cells and produce meaningful visual improvements, evidence that supported moving to a registration trial.
Jean Bennett and Albert Maguire at the University of Pennsylvania led the scientific and surgical development that eventually produced the registration trial. Maguire performed the precise subretinal injections required to deposit the adeno-associated virus vector directly beneath the photoreceptor layer, a technically demanding procedure that distinguishes in vivo gene therapy delivery from any prior treatment. Katherine High, who co-founded Spark Therapeutics to commercialize the work, oversaw the transition from academic research to a regulatory submission. The phase 3 registration trial enrolled 31 patients at two clinical sites, Children's Hospital of Philadelphia and the University of Iowa, a number that reflects the rarity of RPE65 mutations rather than any shortcut in design.
On December 19, 2017, the FDA approved voretigene neparvovec, making it the first gene therapy delivered directly into the human body to clear the agency. The primary endpoint was a bilateral multi-luminance mobility test, a novel instrument the investigators developed specifically for this trial because no validated measure existed for the condition. Treated patients navigated a standardized obstacle course at light levels ranging from one lux to four hundred lux significantly better than controls, and full-field light sensitivity also improved. The approval required a post-marketing registry to collect long-term durability data, an acknowledgment that the follow-up from a 31-patient trial could not answer all questions.
The procedural template Luxturna established, subretinal or targeted tissue delivery, AAV vector serotype selection, single-dose design, and a companion registry requirement, became a reference point for later in vivo gene therapy programs. Regulators and developers alike studied the Luxturna submission when building dossiers for hemophilia B gene therapies and other ocular indications. The approval also forced a conversation about pricing for single-administration curative therapies; Spark listed voretigene at $425,000 per eye, prompting outcomes-based rebate agreements with payers. Longer-term follow-up of the earlier phase 1 cohorts has generally shown the benefit holding up over multiple years.
Keep exploring
 Read next · same disease or problem
First Approved Human Gene Therapy (ADA-SCID, Ashanthi DeSilva) (1990)
The 1990 trial modified cells outside the body, and Luxturna delivered its gene directly inside the eye. The ADA entry shows the first authorized gene therapy, partial in effect but proof that gene transfer could work.
Read this moment
 Today on The Clinical Times
Florida dengue outbreak appears to be largest in continental U.S. in decades
Florida has reported more than 250 locally acquired dengue cases this year, with most in Hillsborough County, according to state health officials.
Read today’s top stories
All 526 moments in the history of medicine. This one is in chapter 7, Genes and pandemics
Connected moments
How this moment links to others in the history of medicine, and what you will find in each.
- Same disease or problem2019Onasemnogene, gene therapy for spinal muscular atrophyBoth use an adeno-associated virus to deliver a working gene in a single dose. The onasemnogene entry shows infants with spinal muscular atrophy surviving without permanent ventilation.Read this moment
- Same disease or problem2026Gene therapy for OTOF deafnessLuxturna injected a gene into the eye to improve sight, and the OTOF therapy infused one into the cochlea to treat deafness. The OTOF entry shows the first dual vector gene therapy the FDA approved.Read this moment
-
 Same disease or problemc. 1290The invention of spectaclesSeven centuries apart, both sought to restore failing sight, one with lenses and one by repairing a gene. The spectacles entry shows the first use of lenses to correct vision.Read this moment