Critical & Organ Care
2013
PROSEVA prone positioning in severe ARDS
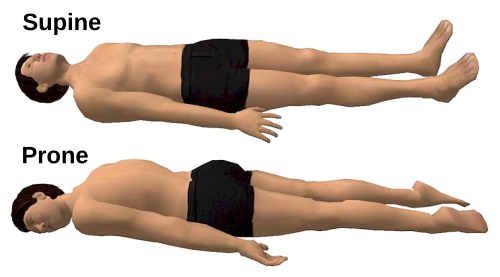
In 466 patients with severe ARDS, daily 16-hour prone sessions cut 28-day mortality to 16.0% from 32.8%. Results held at 90 days and the maneuver was used widely during COVID-19.
Key people
- Claude Guerin
- Principal investigator; designed and led the PROSEVA trial at Croix-Rousse Hospital.
- Jean Reignier
- Second author of the 2013 PROSEVA report.
- Luciano Gattinoni
- Described physiological basis of prone positioning in ARDS; informed PROSEVA design.
Source
The physiological rationale for prone positioning in ARDS has been understood since the 1970s. In the supine position, the dependent dorsal lung regions bear the weight of the edematous lung above them and partly collapse, while the nondependent regions take most of the ventilation and risk overdistension. Turning a patient prone spreads gas and lung stress more evenly, improving ventilation-perfusion matching and reducing cyclical opening and closing of dependent alveoli. What was missing for decades was a trial that could demonstrate whether this physiological improvement translated to a survival benefit.
Several randomized trials in the 2000s tested prone positioning without finding a mortality reduction. Those earlier studies enrolled heterogeneous ARDS populations, several used short daily proning sessions, and they included sites with varying levels of experience in the technique. Claude Guerin at Croix-Rousse Hospital in Lyon identified two factors he believed explained the null results: insufficient session duration and insufficient restriction to the most severely hypoxemic patients.
PROSEVA, which Guerin led, randomized 466 patients with severe ARDS at 26 ICUs in France and one in Spain. Eligibility required a PaO2 to FiO2 ratio below 150 on standardized ventilator settings within 36 hours of intubation. The prone group received sessions of at least 16 consecutive hours per day. Twenty-eight-day mortality was 16.0% in the prone group versus 32.8% in the supine group; at 90 days the figures were 23.6% and 41.0%, respectively. The rate of complications did not differ significantly between the groups. Jean Reignier was second author of the report.
The result was striking in magnitude, but the trial also illustrated why context matters in procedural interventions. The participating units had substantial experience with proning, and the protocol required careful attention to endotracheal tube security, hemodynamic monitoring during turns, and prevention of pressure injuries. Implementing the protocol outside experienced centers risked replicating the intervention without replicating the expertise. This tension between trial results and real-world implementation became a recurring theme when COVID-19 arrived.
During the COVID-19 pandemic, PROSEVA became the principal evidence base for prone positioning in mechanically ventilated patients with COVID-19-associated ARDS, and prone positioning rates in ICUs increased substantially. The protocol was also extended informally to awake, non-intubated patients on supplemental oxygen, a practice the PROSEVA trial did not evaluate and whose effect on outcomes was still uncertain in 2020. The 2017 guideline of the American Thoracic Society, the European Society of Intensive Care Medicine and the Society of Critical Care Medicine made a strong recommendation for prone positioning for more than 12 hours a day in severe ARDS.
Keep exploring
 Read next · same disease or problem
ARDSNet ARMA low tidal volume ventilation trial (2000)
Both cut ARDS deaths by changing how patients are ventilated, gentler volumes in 2000 and lying face down in 2013. The ARMA entry shows mortality falling from 40 to 31 percent.
Read this moment
 Today on The Clinical Times
Florida dengue outbreak appears to be largest in continental U.S. in decades
Florida has reported more than 250 locally acquired dengue cases this year, with most in Hillsborough County, according to state health officials.
Read today’s top stories
All 526 moments in the history of medicine. This one is in chapter 7, Genes and pandemics
Connected moments
How this moment links to others in the history of medicine, and what you will find in each.
-
 Same disease or problem2020RECOVERY Trial: Dexamethasone for COVID-19During COVID-19 proning spread widely for ventilated patients, and RECOVERY found a drug that saved the same group. It shows dexamethasone cutting deaths by about a third in ventilated patients.Read this moment
-
 Same disease or problem1975Extracorporeal membrane oxygenation (ECMO) for neonatal respiratory failure (Bartlett)Both are ways to support lungs failing from severe respiratory disease, turning patients prone or oxygenating blood outside the body. The ECMO entry shows the CESAR trial's benefit in adults.Read this moment