Endocrinology
1998
UK Prospective Diabetes Study (UKPDS 33)
Two 1998 reports from the UK Prospective Diabetes Study: intensive glucose control in 3,867 newly diagnosed patients cut microvascular complications by 25%, and metformin in overweight patients lowered diabetes-related death by 42%.
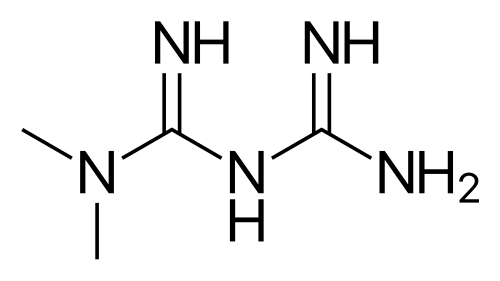
Key people
- Robert Turner
- Oxford physician who led the UKPDS; first author of the 1999 UKPDS 49 report
- Rury Holman
- Oxford Diabetes Trials Unit investigator and first author of the 2008 ten-year follow-up
- Irene Stratton
- Oxford Diabetes Trials Unit researcher and first author of the 2000 UKPDS 35 analysis
Source
When Robert Turner and colleagues at Oxford began recruiting for a long-term diabetes trial in 1977, the treatment of type 2 diabetes rested largely on clinical convention, with little outcome data behind it. Diet was the usual first step, and no large, long trial had shown whether lowering blood glucose reduced complications. There was also concern that sulfonylureas might raise cardiovascular deaths and that high insulin levels might promote atheroma.
The UKPDS recruited 5,102 patients with newly diagnosed type 2 diabetes between 1977 and 1991, and the glucose comparison reported in 1998 randomized 3,867 of them, median age 54, to intensive or conventional policies for about ten years. Intensive glucose control using sulfonylureas or insulin brought median HbA1c to 7.0%, compared with 7.9% in the conventional diet-based group. The intensive group showed a 25% relative reduction in microvascular endpoints, including the need for retinal photocoagulation, and a 12% reduction in any diabetes-related endpoint. A companion paper in the same Lancet issue reported that in 753 overweight patients, metformin cut diabetes-related death by 42% and all-cause mortality by 36% against conventional treatment, and did better than sulfonylureas or insulin for any diabetes-related endpoint, all-cause mortality and stroke.
Because metformin also caused less weight gain and fewer hypoglycemic attacks, the authors suggested it might be the first-line drug of choice for overweight patients. A worrying signal from a smaller add-on study, in which adding metformin to a sulfonylurea raised diabetes-related deaths, was not confirmed in an analysis of 4,416 patients. Intensive control with sulfonylureas or insulin did not significantly reduce macrovascular disease, while the companion UKPDS 38 study found that tight blood pressure control cut diabetes-related deaths by 32% and strokes by 44%.
Rury Holman, who had worked with Turner on the trial, led ten years of post-trial monitoring, reported in 2008. Differences in HbA1c between the groups disappeared within a year, yet in the sulfonylurea-insulin group the reduction in microvascular disease persisted (24%) and reductions in myocardial infarction (15%) and death from any cause (13%) emerged. In the metformin group, myocardial infarction was 33% lower and deaths 27% lower.
An observational analysis of the cohort, UKPDS 35 in 2000, found that each 1% fall in updated mean HbA1c was associated with 21% fewer diabetes-related deaths and 37% fewer microvascular complications. The UKPDS Risk Engine, published in 2001, used the trial's data to estimate coronary risk in type 2 diabetes.
Keep exploring
 Read next · same disease or problem
DCCT (Diabetes Control and Complications Trial) (1993)
DCCT proved tight glucose control prevents complications in type 1 diabetes, and UKPDS tested it in type 2. The DCCT entry shows eye and nerve damage cut sharply at the cost of more hypoglycemia.
Read this moment
 Today on The Clinical Times
Florida dengue outbreak appears to be largest in continental U.S. in decades
Florida has reported more than 250 locally acquired dengue cases this year, with most in Hillsborough County, according to state health officials.
Read today’s top stories
All 526 moments in the history of medicine. This one is in chapter 6, Trials, scanners and rights
Connected moments
How this moment links to others in the history of medicine, and what you will find in each.
-
 Same disease or problem2008ACCORDUKPDS showed moderate tightening helped, and ACCORD found that pushing glucose very low in high-risk patients raised deaths. The ACCORD entry shows its intensive arm halted early.Read this moment
-
 Same disease or problem2015EMPA-REG OUTCOMEUKPDS found metformin cut diabetes deaths, and EMPA-REG was the first trial of a newer glucose drug to lower cardiovascular death. It shows cardiovascular mortality cut by 38 percent.Read this moment
- Same disease or problem1776Dobson's experiments on diabetic urineUKPDS measured glucose control in thousands of patients, two centuries after Dobson showed the sugar of diabetes is in the blood. Dobson's entry shows the evaporated urine that tasted like brown sugar.Read this moment