Neurology & Psychiatry
1987
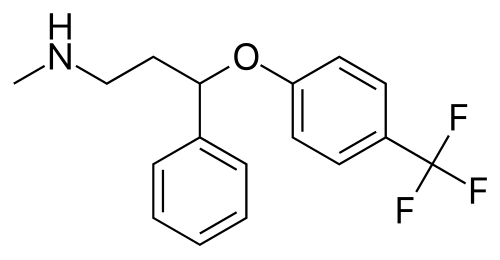
Fluoxetine (Prozac) approval: first widely used SSRI
FDA approval of fluoxetine on Dec 29, 1987 gave clinicians an antidepressant far less lethal in overdose than tricyclics, making drug treatment of depression routine in primary care and vastly more common.
Key people
- David Wong
- Eli Lilly neuroscientist who identified fluoxetine's selective serotonin reuptake inhibition
- Bryan Molloy
- Eli Lilly medicinal chemist who synthesized the fluoxetine compound
- Ray Fuller
- Eli Lilly pharmacologist who established fluoxetine's in vivo serotonergic activity
- Arvid Carlsson
- Swedish pharmacologist whose work on monoamine neurotransmission helped frame the biology underlying SSRI development
Source
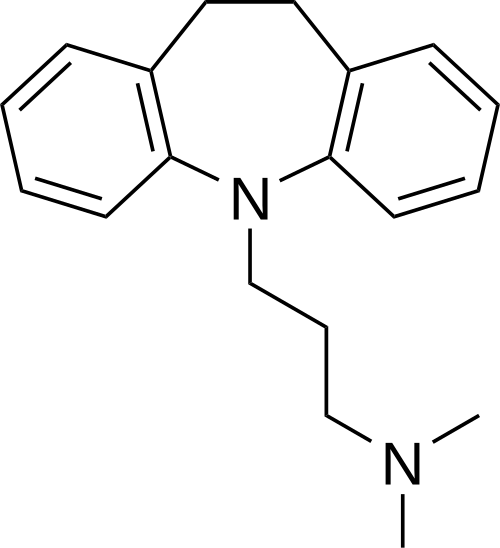
In the two decades before fluoxetine, tricyclic antidepressants were the standard pharmacotherapy for depression. Imipramine, amitriptyline, and their congeners were effective, but their therapeutic window was narrow. A month's supply at a standard dose contained enough drug to cause fatal cardiac arrhythmias in overdose, and patients with major depression and active suicidal ideation were treated with these agents only cautiously, often requiring close monitoring or hospitalization to mitigate the overdose risk. The side effect burden, including sedation, dry mouth, orthostatic hypotension, and weight gain, also limited tolerability and long-term adherence.
The chemistry that produced fluoxetine began with systematic work at Eli Lilly in the early 1970s. Bryan Molloy, a medicinal chemist, synthesized a series of phenoxyphenylpropylamine compounds, and David Wong, a neuroscientist, screened them for selectivity at the serotonin transporter. One compound showed tight binding to the serotonin reuptake site with minimal affinity for norepinephrine, dopamine, histamine, and muscarinic receptors. Ray Fuller, a pharmacologist on the team, confirmed the compound's serotonergic activity in animal models. The molecule, eventually named fluoxetine, advanced through a decade of clinical testing before the FDA granted approval on December 29, 1987.
The clinical difference between fluoxetine and the tricyclics lay mainly in safety margin and side effects; head-to-head trials generally showed similar response rates. The main distinction was the overdose profile. Lethal toxicity with fluoxetine required far higher doses than with amitriptyline or imipramine, which substantially changed the risk calculus for prescribing in patients with suicidal ideation. For the first time, primary care physicians could initiate antidepressant treatment in this population without the same level of concern about providing a lethal means.
Adoption in primary care was rapid, and much of the drug treatment of depression moved from psychiatrists to general practitioners. Other SSRIs followed: the FDA approved sertraline on December 30, 1991, and paroxetine on December 29, 1992. By the mid-1990s, the SSRI class had largely displaced tricyclics as first-line pharmacotherapy for depression, dysthymia, panic disorder, and obsessive-compulsive disorder.
The broader cultural impact was considerable, as fluoxetine became the subject of books, public debate, and legal proceedings regarding its psychiatric effects. Later meta-analyses found that the benefit of antidepressants, SSRIs included, is modest in mild-to-moderate depression and larger in severe illness. In October 2004 antidepressants received a boxed warning about suicidal thinking and behavior in children and adolescents, and in May 2007 the FDA ordered it extended to young adults. Neither of these refinements displaced fluoxetine from clinical use; it remains on the World Health Organization's Essential Medicines List and is still widely prescribed globally.
Keep exploring
 Read next · built on
Imipramine, the first tricyclic antidepressant (Kuhn) (1958)
Fluoxetine replaced tricyclics like imipramine, which worked but could kill in overdose. The imipramine entry shows how Kuhn found the first tricyclic and how its action shaped the monoamine theory.
Read this moment
 Today on The Clinical Times
Florida dengue outbreak appears to be largest in continental U.S. in decades
Florida has reported more than 250 locally acquired dengue cases this year, with most in Hillsborough County, according to state health officials.
Read today’s top stories
All 526 moments in the history of medicine. This one is in chapter 6, Trials, scanners and rights
Connected moments
How this moment links to others in the history of medicine, and what you will find in each.
-
 Same disease or problem2006STAR*D sequenced antidepressant treatment studySTAR*D began with an SSRI and asked what to do when it fails, finding remission fell with each later step. Its entry shows the four-step study and a 2023 reanalysis that lowered its results.Read this moment
-
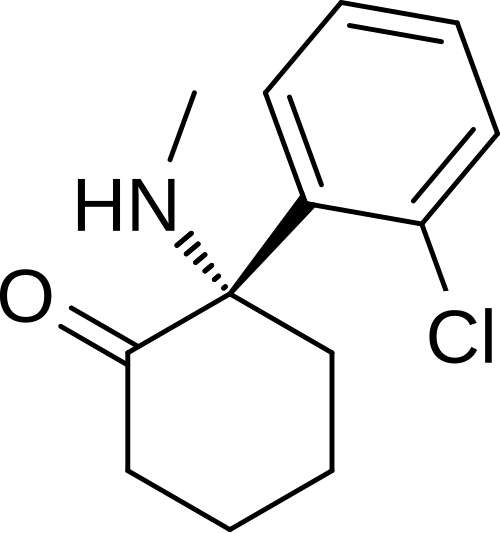 Same disease or problem2019Esketamine (Spravato) for treatment-resistant depressionSSRIs share the monoamine mechanism that esketamine was the first to break from. The esketamine entry shows a nasal spray for depression that standard drugs had failed to relieve.Read this moment